

TL;DR
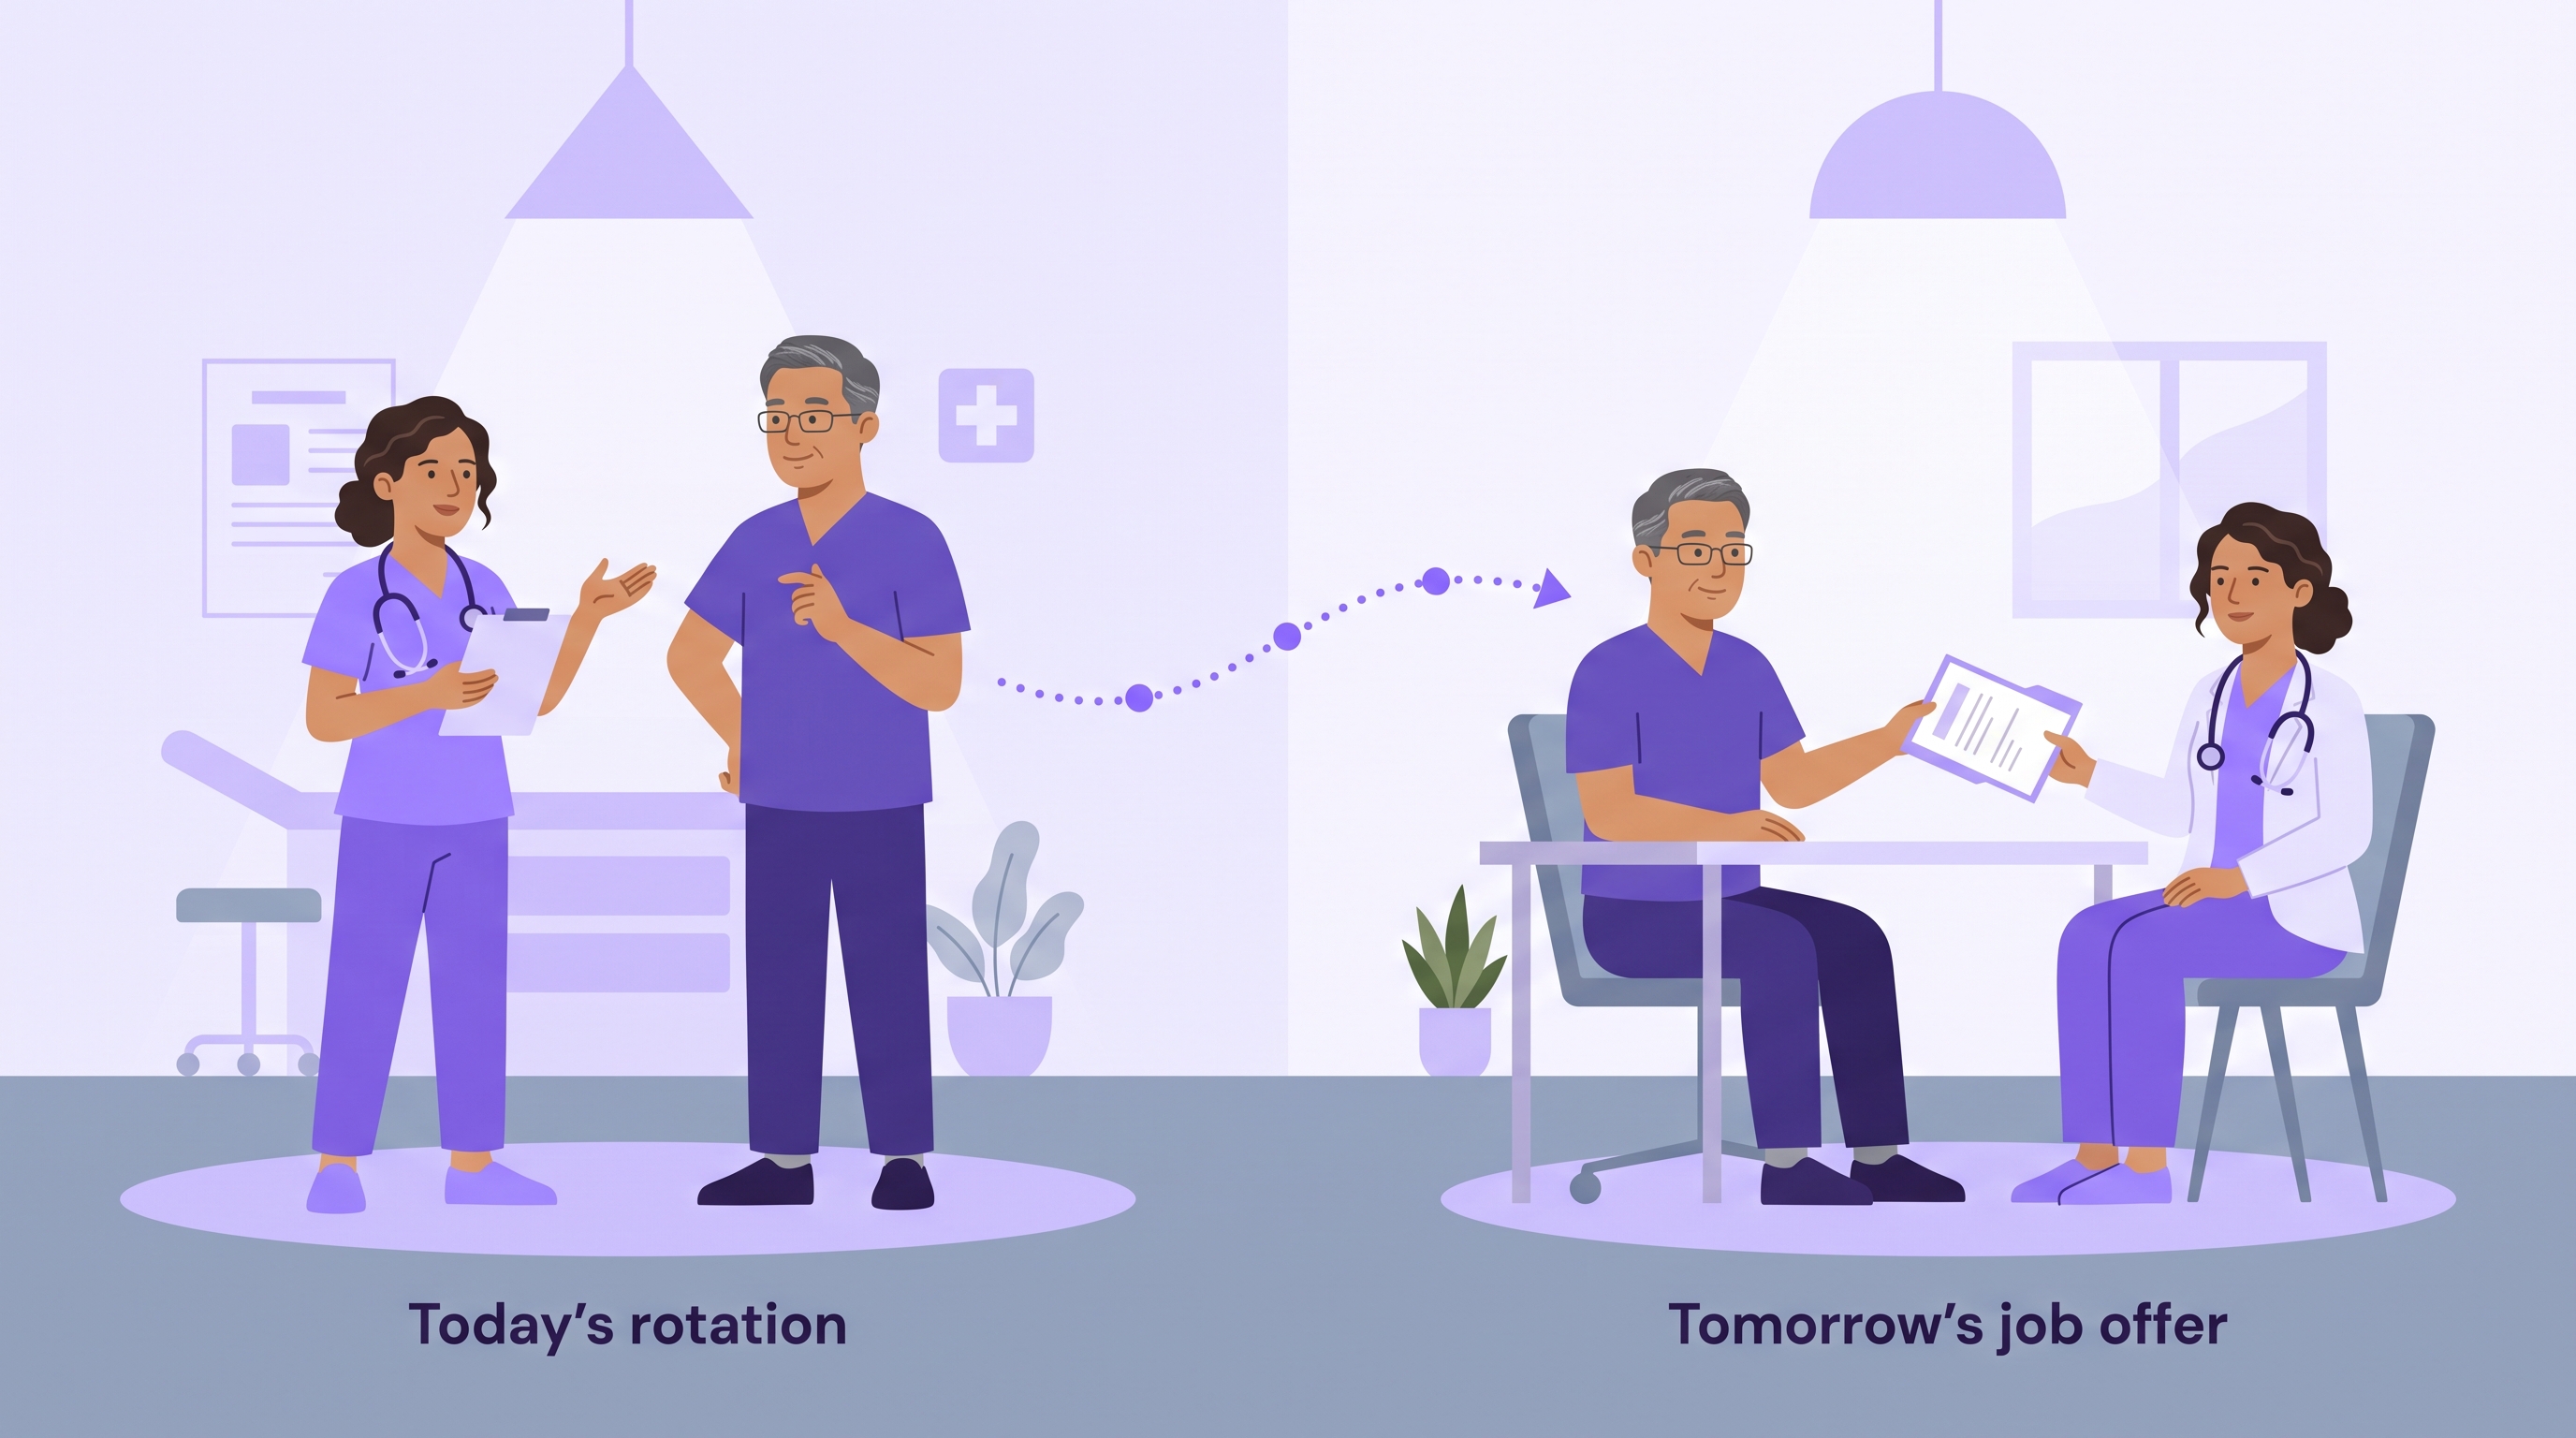
- Clinical placement is the front of the NP workforce pipeline, not just a compliance task: The rotation a student completes today is often the first step toward the position they hold two years from now, which means placement decisions shape workforce outcomes long after graduation.
- The clinical site is frequently the first employer: Precepting increasingly functions as recruitment, health systems observe a candidate for weeks or months before a single résumé changes hands, and many nurse practitioners receive their first job offers directly from a rotation site.
- Placement design shapes regional workforce outcomes: Specialty fit, geography, and relationship continuity influence which specialties graduates can enter, where they choose to practice, and how quickly they reach full productivity.
- Programs that measure placement-to-hire turn placement into a reputation and enrollment asset: Tracking how many rotations convert to job offers reframes clinical coordination from an administrative cost into a workforce metric leaders and accreditors care about.
- NPHub sources and vets the placement layer; NPHire connects graduates to employers: Together they support the full rotation-to-hire pathway without asking faculty to run recruitment on top of teaching.
NP clinical placement is usually treated as a cost or compliance problem, a paperwork and scheduling burden that strains faculty and worries accreditors. That view is accurate but incomplete. Clinical placement is also the front of the nurse practitioner workforce pipeline, the point where a nursing student takes the first step toward becoming a hire. Most coverage stops at the cost-and-compliance framing and misses where placement actually sits in the larger system.
Clinical placement is the entry point to the nurse practitioner workforce pipeline. Before a graduate becomes a new hire at a clinic or health system, they were a student in a clinical rotation somewhere, assessing patients, presenting cases, and being watched by the exact people who later decide whom to hire. Rotations are working auditions. The site is often the first employer. And that truth aligns two groups that usually sit on opposite sides of the placement conversation: the programs that need capacity and the health systems that need providers.
This piece looks at placement through that shared lens. It covers how clinical rotations turn into job offers, why a growing number of health systems now treat precepting as recruitment, how placement design influences regional workforce outcomes, and how program leaders can measure the rotation-to-hire pathway instead of leaving it to chance.
If you are trying to see where your own pipeline leaks which rotations convert to hires and which quietly stall a semester short, the NPHub university partnerships team maps that with programs directly, no commitment attached. It is a useful first conversation even if the answer turns out to be something you build in-house.
What is the connection between nurse practitioner clinical placement and the workforce pipeline?
Clinical placement is the top of the NP workforce funnel. Every practicing nurse practitioner completed supervised clinical rotations first, and those rotations do more than satisfy an hours requirement, they determine which specialties a graduate can credibly enter, which references they carry, and, in many cases, which employer makes the first offer. Treating placement as the front of the pipeline, rather than a task at the end of a checklist, changes how a program values it.
A student needs a placement to complete the required clinical hours. The quality and specialty of that placement shape the skills and patient exposure they develop. The relationships they build during the rotation become their professional network. And that network is where a large share of first job offers originate. Nurse practitioner education, in other words, does not hand the workforce a finished product at graduation; it feeds candidates into local health care through the placements arranged years earlier.
That connection is only becoming more consequential as demand climbs. The U.S. Bureau of Labor Statistics projects nurse practitioner employment to grow roughly 40% from 2024 to 2034, from about 320,400 jobs to 448,800, making it one of the three fastest-growing occupations the agency tracks, with an estimated 29,500 openings a year. Each of those openings is a position a program graduate could fill. Labor statistics describe demand; clinical placement is the mechanism that turns a nursing student into someone who can meet it.
Why are health systems starting to treat precepting as recruitment?
A growing number of health systems now see precepting as an early stage of their recruitment process rather than a favor to a nearby school. A clinical rotation gives an employer weeks or months of direct observation, far more signal than any interview or résumé, at a moment when the NP labor market is competitive and every reliable hiring channel matters. When the rotation ends, the employer already knows whether the candidate fits the team, the patient population, and the work culture.
Recruiting nurses and advanced practice providers is expensive, and turnover is even more expensive. A hire who trained on-site arrives already oriented to the electronic records, the workflows, the specialty, and the people, which compresses ramp-up time and reduces the risk of an early departure. Precepting turns a source of uncertainty—will this new hire work out?—into something the employer has already assessed firsthand.
The evidence from structured academic-practice partnerships is striking, even where the roles are RNs rather than NPs. In one nurse apprenticeship program documented by the American Association of Colleges of Nursing, roughly 90% of graduates joined the organization where they trained, without any contract requiring it, and 92% stayed beyond their first year. Another health system that embedded a nurse recruiter inside its partner college of nursing raised new-graduate hiring from about 32% to 57% over two years while cutting turnover from 17% to 12%. Those numbers describe the same underlying mechanism that makes precepting attractive for NP roles: when clinical training and hiring share the same footprint, retention improves, and recruitment efforts get cheaper.
For health systems facing primary care physician shortages and rising patient demand, that makes NP rotations a strategic pipeline, not a community obligation. Preceptors are, in effect, evaluating future colleagues.
How do clinical rotations turn into job offers?
Clinical rotations turn into job offers because they function as extended, real-world interviews. Over a rotation, hiring managers and preceptors watch a student's clinical reasoning, communication with patients, collaboration with staff, and ability to handle volume and complexity under supervision, demonstrated skill that carries more weight than anything on a résumé. When a position opens, the student who already knows the team and has proven reliable is the obvious candidate.
The conversion tends to work through a few consistent mechanisms:
- Capstone and final rotations act as auditions: Autonomy grows across a program, so by the final rotations a student is managing patients much like a practicing provider. That is precisely when an employer can see what the person will actually do on day one.
- Demonstrated skill beats a paper application: A strong rotation gives an employer weeks of evidence. Candidates who trained on-site skip the guesswork that makes hiring an unknown applicant risky.
- Preceptors become references and connectors: A preceptor who trusts a student's judgment will vouch for them, forward openings, and introduce them to hiring managers, often before a role is ever posted.
- Familiarity lowers turnover: New hires who trained where they were hired already understand the work culture and expectations, so they are less likely to leave in the first year, which is exactly the outcome employers optimize for.
None of this is guaranteed, and no program should promise it. But the pattern is well established: many nurse practitioners land their first position through a clinical rotation connection. A placement is not only a requirement to satisfy, but it is also the single best opportunity a student has to show an employer what they can do.
How does placement design shape regional workforce outcomes?
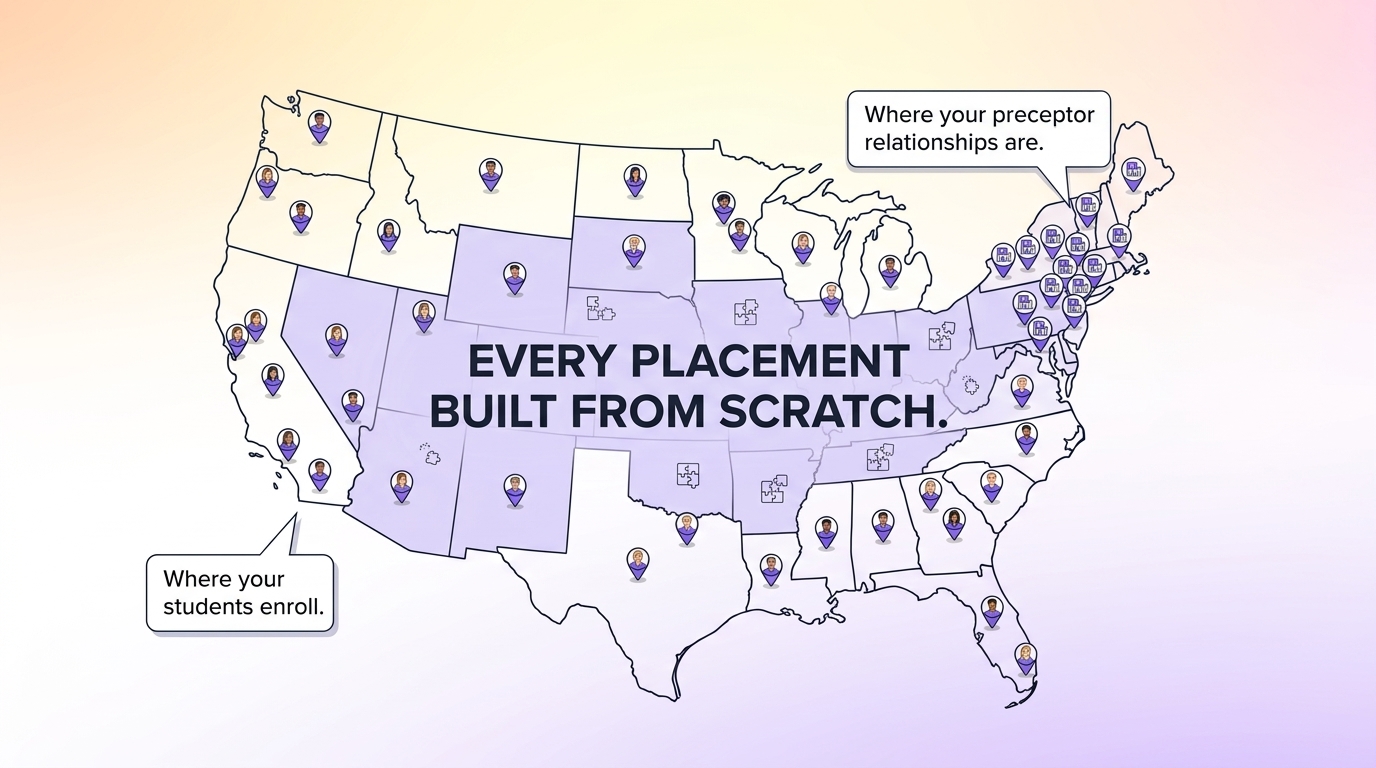
Placement design, which specialties, which sites, which regions, and how continuously the program maintains those relationships, directly shapes where graduates end up practicing. A rotation is not just an educational box to check; it nudges the graduate's first specialty, their comfort with a given patient population, and often the geography of their career. Thoughtful placement design turns individual rotations into a workforce strategy for the surrounding community.
- Specialty fit is the clearest lever: Employer demand is heaviest where preceptors are hardest to find: psychiatric-mental health, adult-gerontology primary care, and hospital-based critical care and acute care. When a program can consistently place students into those high-demand specialties, it produces graduates prepared to fill the exact roles a region is short on. When it cannot, students default to whatever placement is available, and the workforce gap in the shortage specialties persists.
- Geography matters just as much: Research on clinical placements finds that where and how students train influences attrition, the conversion from student to practicing clinician, and where graduates choose to work after licensure. A student who rotates through a rural clinic or an underserved community health center gains both the specialized skills and the professional credibility to build a career there and is far more likely to stay. Well-designed placement is one of the few tools a program has to strengthen its regional workforce rather than simply export graduates elsewhere.
Programs and health systems that want placement to feed regional hiring, not just satisfy an hours requirement, can work through that design with the NPHub university team: which specialties to prioritize, which sites convert to offers, and where dedicated capacity would move both graduation and hiring numbers. It is a planning conversation, not a pitch.
How do placement models affect the rotation-to-hire pathway?
The placement model a program uses (school-placed, self-placed, or a hybrid) shapes how reliably rotations translate into hires. School-placed models give the program control over specialty fit, site quality, and continuity, which are the same variables that determine whether a rotation becomes a job offer. Self-placed models shift that burden onto students and, with it, much of the influence over where the pipeline ultimately leads.
The mechanics of clinical rotations are the design surface here. Most NP programs now require 750 direct patient care hours at the master's level and 1,000 total practice hours for DNP programs, typically spread across several sites and two to three clinical days a week. Each site is a potential first employer. A program that treats site selection as pipeline design, matching students to settings with strong teaching cultures, sufficient patient volume, and hiring capacity, stacks the odds in its favor. A program that treats it as filling a slot leaves those outcomes to chance.
Self-placement is where the pathway most often breaks. When a program relies on students to find their own preceptors, placement quality varies with each student's personal network, the strongest sites are not reliably in reach, and the program loses visibility into which rotations lead anywhere. The result is uneven clinical experiences, thinner compliance records, and a rotation-to-hire pathway the program cannot see, let alone manage. Keeping placement inside a system the program controls is what makes the pathway measurable and improvable.
What role do academic-practice partnerships play?
Academic-practice partnerships bridge a program's placement pipeline and a health system's hiring needs. When a nursing school and a clinical partner formalize their relationship (shared goals, defined roles, tracked metrics), clinical placement stops being a series of one-off asks and becomes shared infrastructure that both sides have a stake in maintaining. That structure lets precepting reliably feed recruitment.
The strongest partnerships treat the preceptor network as a jointly owned asset. Rather than rebuilding relationships every semester, the program and the health system develop a standing pipeline of experienced preceptors, maintain it across cohorts, and use it to plan for future staffing needs. The AACN's work on sustainable partnerships is explicit on this point: collaborations succeed when partners commit to shared goals, track success with clear metrics, and extend the relationship beyond individual student placements into workforce planning and quality improvement, work that often ends up documented in nursing journals and shared across institutions.
Site responsiveness is a useful early signal of partnership health. A clinical site that replies quickly, approves placements smoothly, and offers rotations in the specialties a program needs is usually a site that also hires. Tracking which sites are responsive and which consistently convert rotations into offers tells a program where its most productive workforce relationships already exist. Those are the partnerships worth formalizing and protecting, because they are where the pipeline actually flows.
Why do preceptor incentives matter and how does "precepting as recruitment" change the math?
Preceptor incentives matter because the supply of clinicians willing to teach is the binding constraint on the entire pipeline, roughly 60% of practicing NPs are not currently precepting, with "never being asked" and employer restrictions among the top reasons. But once precepting is understood as recruitment, the incentive math changes. For a health system, the strongest incentive is no longer an external reward; it is the hiring funnel itself.
That reframing is the most important one in this article. A clinic that precepts a strong student gains a low-cost look at a potential hire, a shorter future onboarding, and a better retention bet. In that framing, the "compensation" for precepting is a recruitment channel that is cheaper and more reliable than posting a job and screening strangers. This is why health systems increasingly build precepting into their workforce strategy rather than treating it as charity: the return shows up in their own hiring numbers.
Non-monetary levers still matter, and programs should use them to sustain the relationship over time:
- Recognition and continuity: Clinicians who feel valued (thanked, kept informed, invited back) precept again. Relationship continuity is itself an incentive.
- CME credit and stipends: Where budgets allow, continuing education credit or modest stipends acknowledge the real time precepting takes and help clinicians justify it against their own productivity targets and work-life balance.
- Training and mentorship support: Preparing preceptors to teach, not just supervise, improves the student experience and the preceptor's own sense of purpose, and better-prepared preceptors produce more hire-ready graduates.
- Professional community: Connecting preceptors through professional associations and program events turns a transactional favor into a professional identity worth maintaining.
The goal is not to buy precepting one rotation at a time. It is to make precepting worth a clinician's genuine interest, so the relationship and the pipeline it feeds renew cohort over cohort.
How can NP programs measure placement-to-hire outcomes?
Programs can measure placement-to-hire by tracking, for each cohort, what share of clinical rotations lead to a job offer at or through the rotation site. That single conversion rate turns clinical placement from an invisible administrative function into a workforce KPI, one that deans, health system partners, and accreditors all understand. What gets measured gets managed, and placement-to-hire reframes placement as an asset rather than a cost.
A workable measurement approach rests on a few operational moves:
- Give sourcing and placement a dedicated owner: A named recruiting or placement function, separate from the coordinator managing active rotations, is what makes consistent tracking possible in the first place.
- Maintain a living preceptor and site database: Record specialty, geography, responsiveness, and hiring history for every site, so the program can identify which relationships actually convert.
- Track the conversion, not just the placement: Follow graduates far enough to capture where they were hired and whether the rotation site was involved. Even a rough figure is more than most programs have today.
- Report annually to stakeholders: Fold placement-to-hire, time-to-placement, and site responsiveness into the same reporting cadence used for accreditation and enrollment. It gives leadership a workforce story backed by numbers.
A program that can reliably show it converts rotations into regional hires has a genuine advantage, with prospective students weighing where to enroll, health system partners deciding where to invest, and accreditors assessing the quality and outcomes of clinical education. Placement-to-hire is where a program's clinical infrastructure becomes visible as a workforce contribution.
How NPHub and NPHire support the rotation-to-hire pathway
The rotation-to-hire pathway has two ends, and NPHub and NPHire support both. NPHub handles the placement layer by sourcing, vetting, and coordinating the clinical rotations that put students in front of future employers. NPHire handles the hiring layer with an NP-exclusive platform that connects graduates with the employers actively recruiting them. The point is to keep faculty out of the recruitment business on one end and keep graduates from disappearing into a generic job market on the other.
On the placement side, the work is deliberately clinician-led. Board-certified nurse practitioners source and vet every preceptor through a structured NP-to-NP interview that evaluates scope, specialty, and patient population; credentials and licensure are screened with zero tolerance for restrictions; clinical sites are approved separately from the individual preceptor; and active placements are re-verified every 45 days as conditions change. The result is capacity a program can lean on and documentation that holds up under review, without the sourcing scramble landing on faculty.
On the hiring side, NPHire gives graduates a place to land built specifically for advanced practice roles, where the placement pipeline is meant to lead. Programs get a more complete picture of the pathway, from a vetted rotation to a first position, rather than losing track of graduates the moment they walk across the stage.
To build a rotation-to-hire pathway your program can actually see and measure, get in touch with the NPHub university team, led by Director of Business Development Nicholas Carrizales. The conversation starts with where your placement process is holding up, where it is straining, and what a program-owned, hire-aware model would change about both.
Frequently Asked Questions
Do clinical rotations lead to job offers for NP students?
Often, yes. Many nurse practitioners receive their first job offer directly from a clinical rotation site or through a preceptor connection. A rotation functions as an extended interview: hiring managers observe a student's clinical reasoning, communication, and reliability over weeks, which carries more weight than a résumé. No program should guarantee a hire, but a strong rotation is a student's best opportunity to earn one.
Can precepting reduce nurse and NP recruitment costs?
It can. Recruiting and onboarding are expensive, and early turnover is more expensive still. Structured academic-practice partnerships have shown high conversion from trainee to employee and meaningfully lower turnover among clinicians who trained where they were hired. By turning a rotation into a vetted, ramp-ready candidate, precepting reduces both the cost and the risk of the recruitment process.
How do NP programs track placement-to-hire rates?
By recording, for each cohort, what share of clinical rotations result in a job offer at or through the rotation site. Doing this well requires a dedicated placement owner, a maintained database of sites and their hiring history, and enough follow-up with graduates to capture where they were hired. Reported annually alongside time-to-placement and site responsiveness, it becomes a workforce KPI that leaders and accreditors can act on.
What NP specialties have the strongest rotation-to-hire pathways?
The specialties where employer demand most outpaces supply tend to convert best: psychiatric-mental health, family practice, adult-gerontology primary care, and hospital-based acute and critical care. Demand in these areas is driven by physician shortages, an aging population, and a national mental health crisis, so graduates who complete strong rotations in them are well positioned for job offers, provided the program can secure those placements in the first place.
What is the difference between a clinical rotation and a job interview?
A traditional interview is a brief, self-reported snapshot; a clinical rotation is weeks of observed performance. During a rotation, a preceptor and site see a student manage real patients, document care, and work within a team. That is why rotations are described as working auditions, they give an employer evidence an interview cannot, which is exactly why so many first positions originate from them.
How does placement design affect where NP graduates end up working?
Placement design influences a graduate's first specialty, their comfort with specific patient populations, and the geography of their early career. Students who rotate through a particular setting (rural primary care, a community mental health clinic, an inpatient critical care unit) build the skills, references, and credibility to work there. Programs can use this to strengthen the regional workforce rather than simply produce graduates who practice elsewhere.
Should NP programs let students find their own clinical placements?
Self-placement tends to produce uneven outcomes. It shifts sourcing onto the students with the least time and leverage, makes placement quality depend on personal networks, and leaves the program without visibility into which rotations lead to hires. A program-owned placement process generally produces more equitable clinical experiences, cleaner documentation, and a rotation-to-hire pathway the program can actually measure and improve.
How do academic-practice partnerships support the workforce pipeline?
Formal partnerships turn placement into shared infrastructure. When a school and a health system commit to shared goals, maintain a standing preceptor network, and track outcomes together, precepting reliably feeds recruitment and retention. The strongest partnerships extend beyond individual placements into joint workforce planning, so the same relationship serves both the program's capacity needs and the health system's hiring needs.
Find a preceptor who cares with NPHub
Book a rotation