

TL;DR
- Most programs can tell you how many students they placed. Few can tell you how well: Placement counts confirm that rotations happened. They say nothing about how long each one took to secure, whether the site was a genuine fit, or whether the preceptor will still be available next cohort. That gap between activity and quality is where clinical placement data earns its keep.
- The metrics that matter are the ones no spreadsheet shows on its own: Time-to-placement, preceptor retention, site capacity utilization, documentation completeness, and student-reported quality tell a program whether its clinical placement process is healthy or quietly straining.
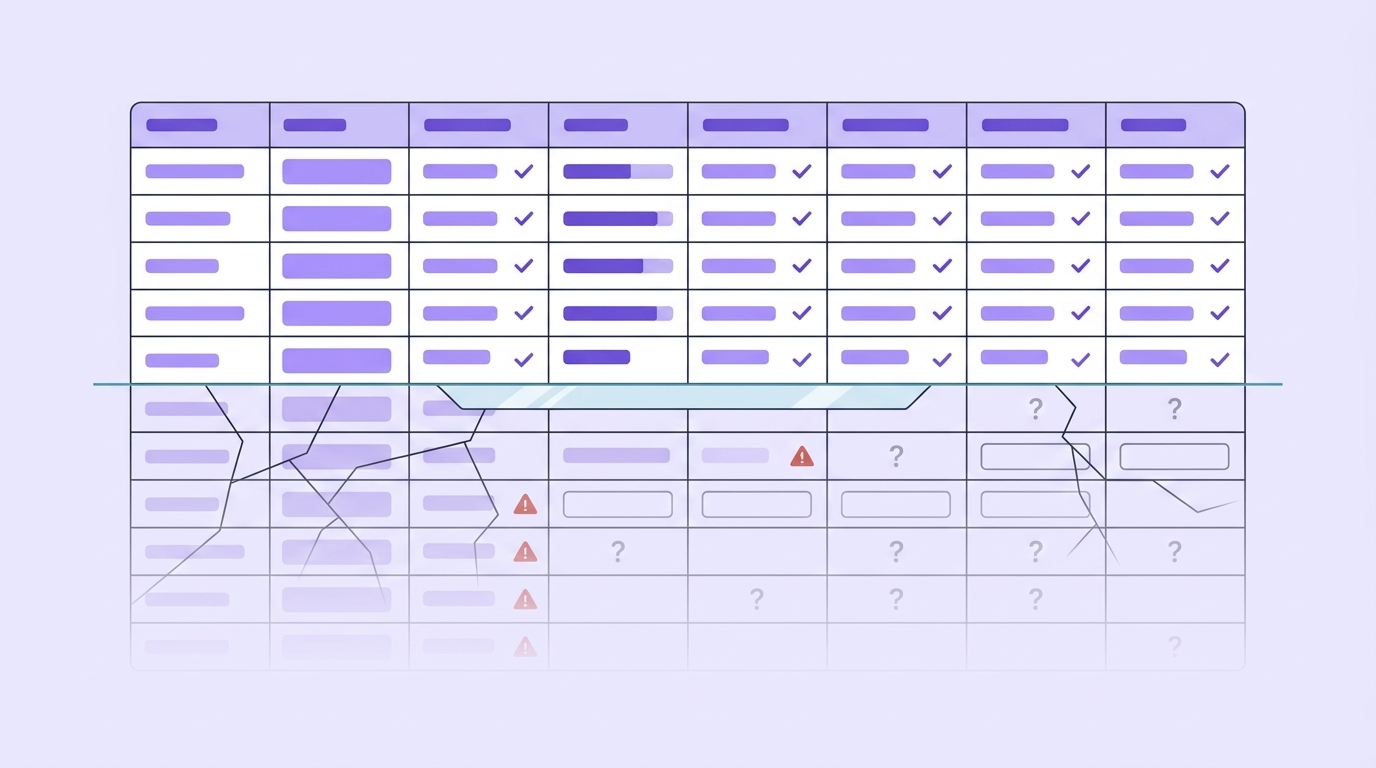
- Spreadsheets record; they do not reveal: A static file can hold a placement history, but it cannot flag an expiring affiliation agreement, warn that a specialty is running short before the term starts, or produce a full compliance record for a random rotation from three cohorts ago in under an hour. That is why clinical coordination is moving toward systems that report, not just store.
- Visibility is what makes capacity defensible: Programs that can see their clinical placement data can defend it under CCNE or ACEN review, plan enrollment against real site availability, and make informed decisions instead of reacting to the next shortage.
- NPHub's recruiting function produces this data as a byproduct: Because clinician-led sourcing, structured NP-to-NP vetting, credential and license screening, separate site approval, and 45-day re-verification are built into how placements are made, the documentation is generated as the work happens rather than assembled under audit pressure. To see how that visibility would map to your program, get in touch with the NPHub university partnerships team.
Once a nursing program stops treating clinical placement as a scheduling task and starts treating it as infrastructure, a new question surfaces almost immediately: Can we actually see what is happening across our rotations?
Most programs cannot, at least not in the way they assume. They can produce a number. Students placed this term. Rotations filled. Hours logged. What they usually cannot produce is the shape behind that number. How long did each placement take to confirm? How many preceptors returned from last cohort versus how many were sourced from scratch? Which clinical sites are near capacity, and which specialties are one retirement away from a gap? Counting placements answers whether. It does not answer how well, and "how well" is the entire question when placement quality shapes student outcomes, faculty workload, and accreditation standing at the same time.
This piece looks at what good clinical placement data looks like, which metrics NP programs should track, and why clinical coordination is steadily moving off spreadsheets and toward reporting that reveals rather than records. If your program wants real visibility into its clinical placement process before the next accreditation cycle or enrollment decision, the NPHub university team works with programs on exactly that.
What is clinical placement data?
Clinical placement data is the structured record of every rotation a program runs: the sourcing timeline, the preceptor and clinical site credentials, the compliance documentation, and the quality signals students and preceptors report afterward. Good placement data captures not only that a rotation occurred, but how it was secured, whether the site and preceptor were verified, and how the clinical experience actually went.
It helps to split the record into two layers, because programs are usually strong on one and blind to the other.
- Activity data answer the question, did it happen? Placements confirmed, clinical hours completed, affiliation agreements signed, students assigned. This is the layer most programs already track, because it maps neatly onto rows in a spreadsheet.
- Health and quality data answer the question, how well did it happen? Time from request to confirmed placement, preceptor return rate across cohorts, documentation completeness, mid-rotation stability, and student-reported quality. This layer reveals whether the clinical placement process is durable or running on borrowed time.
A program operating on activity data alone can look healthy right up until the term a key preceptor declines, a site hits capacity, or a reviewer asks a question the records cannot answer. The quality layer turns placement history into data-driven insights.
Clinical placement process: What's the difference between tracking placements and measuring placement health?
Tracking placements counts outputs. Measuring placement health examines the conditions that produce those outputs, so a program can tell whether this term's results will hold next term. A program can hit its placement numbers every cohort and still be one departure or one audit away from a crisis, because the count says nothing about speed, stability, or fit.
The distinction is easiest to see side by side:
The left column is a scoreboard. The right column is diagnosis. A scoreboard tells you that you won this term. Diagnosis tells you whether your approach is sustainable, and it is the difference between a program that reacts to shortages and one that anticipates them. Research on placement quality is blunt about the stakes: placement experience influences attrition, whether students convert to practicing clinicians, and where graduates ultimately choose to work. The quality of a clinical placement does not stop mattering at graduation. It shapes the workforce the program feeds.
What clinical placement metrics should NP programs actually track?
The clinical placement metrics that matter most fall into seven categories, each answering a question a placement count cannot. Together they tell a program whether its clinical placement management is fast, reliable, compliant, and producing genuine learning, rather than simply filling slots.
- Time-to-placement and on-time start rate: How many days from a student's request to a confirmed placement, and what share of students start their clinical rotations on schedule. This is the speed metric, and speed is throughput. When even a fraction of a cohort waits an extra term to begin clinical coursework, graduation timelines slip in aggregate. Nearly 40% of NP students have delayed graduation by at least one semester because of placement and course-sequencing problems, and every delayed semester defers a tuition cycle and delays workforce entry.
- Preceptor retention and return rate: What percentage of preceptors take a student again in the next cohort, rather than being re-sourced from zero. Retention is the clearest signal of pipeline health. A program that rebuilds its preceptor network every term is running in place; one that retains relationships across cohorts is compounding capacity.
- Site capacity utilization and specialty coverage: How close each clinical site is to its ceiling, and where specialty demand is outrunning supply. Because clinical hours are non-negotiable, site availability, not classroom space, is the real limit on how many nursing students a program can responsibly graduate. Tracking coverage across family practice, women's health, pediatrics, adult-gerontology, and psychiatric mental health exposes the bottleneck before admissions walks into it.
- Documentation completeness and audit-readiness: What share of active placements have current, retrievable records: preceptor qualifications, signed affiliation agreements, separate clinical site approval, and evidence of ongoing faculty oversight. This metric determines whether accreditation review is a report you run or a scramble you survive.
- Student-reported placement quality: How students rate the clinical experience at the midpoint and after the rotation: patient volume, case mix, teaching quality, and whether the setting supported the required competencies. This is the "how well" layer in its purest form, and it is invisible unless a program deliberately collects it.
- Placement stability and mid-rotation disruptions caught: How many rotations ran without interruption, and how many potential problems (a license lapse, a staffing change, a shift in patient population) were caught before they derailed a student. Stability is a risk metric. A placement that was sound in week one is not guaranteed to be sound in week six.
- Outcome correlation: Whether placement quality tracks with downstream student outcomes: program completion, licensure exam pass rates, competency assessments, and career readiness. This is where clinical placement data connects to the program's mission and to workforce planning, and it is the metric accreditors increasingly want to see programs reasoning about.
No program needs a hundred metrics. It needs these few, tracked consistently across every clinical placement, so that patterns become visible before they become findings.
How do you measure clinical placement quality (not just quantity)?
Clinical placement quality is measured through structured feedback loops paired with outcome correlation. Preceptor evaluations after each rotation, student surveys at the midpoint and again at completion, and site ratings that update over time turn subjective impressions into a trackable quality signal that the program can test against student progress and success.
In practice, that means building three habits into the clinical placement process:
- Preceptor evaluations after every rotation: Not to grade the preceptor, but to capture whether the pairing worked, whether the case load matched the program's clinical requirements, and whether the preceptor would take another student.
- Student surveys at mid-rotation and post-rotation: Mid-rotation surveys catch problems while there is still time to intervene. Post-rotation surveys build the historical record. Both should feed a site rating that grows more accurate with each cohort.
- Correlation with student outcomes: A quality signal only earns trust when it predicts something. Programs that connect placement ratings to completion, licensure pass rates, and competency assessments can tell which clinical sites genuinely prepare students and which merely fill a requirement.
Done consistently, this is what lets a program say not just that it placed its students, but that it placed them well, and prove it.
The administrative burden: Why are spreadsheets no longer enough for clinical placement management?
A file can hold a complete placement history and still be unable to warn you that an affiliation agreement expires next month, that a preceptor's license lapsed mid-rotation, or that psychiatric mental health coverage is one departure from a gap. As programs scale, the manual, email-and-spreadsheet approach becomes the bottleneck it was meant to solve.
The failure modes are predictable:
- They are static: A spreadsheet reflects the moment it was last updated, not the current state. By the time someone notices a missing document, the deadline has often passed.
- They are siloed: Placement lives in one file, compliance in another, evaluations in a third, and no one can see the whole picture without stitching them together by hand.
- They do not alert: Nothing prompts a coordinator when a credential is about to lapse or a renewal is due. The system depends entirely on someone remembering to look.
- They break at scale: What works for a small cohort collapses under hundreds of placements across multiple specialties, sites, and compliance requirements.
- The knowledge walks out the door: When a coordinator leaves, the context behind the cells often leaves with them, and the relationships and institutional memory are expensive to rebuild.
Structured reporting changes not the data itself, but what the program can do with it: see live placement status across every rotation, receive alerts on agreement renewals and credential lapses before they become compliance problems, and forecast rather than react. This is the shift clinical coordination is making right now, and it mirrors what allied health and other health sciences programs are already discovering as their own cohorts grow. Moving from storage to reporting is what turns clinical placement management from a filing task into strategic planning.
How can programs use placement data to forecast capacity and prevent bottlenecks?
Programs use clinical placement data to forecast capacity by comparing projected student demand against real clinical site availability, so gaps surface before a term begins rather than mid-program. The same data lets coordinators spot specialty shortages early, sequence placements by student readiness, and flag compliance issues automatically instead of discovering them during review.
Four uses turn placement data into foresight:
- Forecast demand against site capacity: Model next cohort's rotation needs against known site ceilings and preceptor availability. A program that can see the gap in spring can close it before fall, instead of admitting a class it cannot place.
- Spot specialty gaps before the term starts: Coverage data exposes the specialties where demand consistently outruns supply, so outreach starts early in the exact areas that break first.
- Prioritize placements by student readiness: When some students are further along in clinical requirements or background checks, readiness data lets coordinators assign placements in the order that keeps the most students on track.
- Flag noncompliant records automatically: Rather than auditing by hand, the program surfaces missing documents, lapsed credentials, or unsigned affiliation agreements as they occur, keeping records defensible in real time.
This is what data-driven insight looks like in a placement context: fewer surprises, earlier interventions, and enrollment decisions grounded in what the clinical infrastructure can actually support.
What clinical placement data do CCNE and ACEN reviewers expect?
CCNE and ACEN reviewers expect placement records that are documented, repeatable, and retrievable on demand: preceptor qualifications, current signed affiliation agreements, evidence that each clinical site was approved on its own merits, and proof of ongoing oversight across the full rotation. Reviewers are no longer satisfied that students completed their hours. They want to see how each placement decision was made and defended.
The scrutiny tends to land in predictable places:
- Preceptor qualification records: active, unrestricted licensure, board certification, and evidence of clinical fit for the rotation.
- Affiliation agreements: current, signed, and matched to the rotations they cover.
- Clinical site approval: documentation that the site itself was vetted for educational fit, separate from the individual preceptor.
- Ongoing oversight: evidence that conditions were re-checked during the rotation, not confirmed once and forgotten.
Expectations here have tightened. The Sawyer Initiative pushed CCNE to strengthen its standards around clinical site preparation, preceptor qualifications, and rotation quality, particularly for distance-education programs, which raised the bar for what counts as an adequate clinical placement process. The honest gut-check for any program: if a reviewer asked for full documentation on a randomly selected rotation from three cohorts ago, could you produce it within an hour? Programs that can answer yes are the ones whose placement data was built to be retrieved, not reconstructed.
How NPHub gives programs visibility into their placement data
NPHub generates clinical placement data as a byproduct of how placements are made, rather than as a report assembled after the fact. Because sourcing and vetting follow a structured, continuous process, each step produces a specific, verifiable record, so the documentation programs need for compliance and planning already exists when they ask for it.
Five operational pillars each leave a data trail:
- Clinician-led recruiting produces a quality signal. Board-certified nurse practitioners source and vet every preceptor, so fit is evaluated as a clinical judgment and recorded as one, not reduced to a credential check.
- The structured NP-to-NP vetting interview produces fit data. Every prospective preceptor completes a focused conversation on scope, specialty, patient population, and teaching readiness, which becomes a documented record of why a placement was considered a match.
- Credential and license integrity screening produces the compliance record. Active licensure, board certification, and disciplinary history are verified for every preceptor, with any restriction triggering disqualification, so the qualification documentation is complete by default.
- Separate clinical site approval produces site-viability data. Because the site is vetted independently of the individual preceptor, the program has evidence of educational fit and administrative readiness that stands on its own under review.
- 45-day re-verification produces a living audit trail and a stability signal. Active preceptors and sites are re-checked on a set cadence, so changes in license status, scope, or setting surface early and the record reflects the current state, not a snapshot from onboarding.
The result is visibility programs can lean on: audit-ready records that can be produced on demand, faculty kept out of the sourcing and documentation business, and a clinical placement process whose data holds up when it matters. If you want to see how that would map to your cohort size, specialty mix, and graduation timeline, the NPHub university partnerships team, led by Director of Business Development Nicholas Carrizales, works through exactly that with programs. It is a conversation, not a pitch, and a useful one even if you are only mapping where your current process is straining.
Visibility is infrastructure, too
Counting placements tells a program about its past. Measuring them tells a program whether its model will hold. That is the real shift behind the move from spreadsheets to reporting, and behind the questions leaders are starting to ask about clinical placement: not just did we fill the rotations? But can we see, defend, and plan around how we filled them?
Programs that can see their clinical placement data can defend it under accreditation review, forecast capacity against real site availability, and grow enrollment without walking into a placement crisis a semester later. Programs that cannot are managing one of their most consequential operational areas in the dark. As NP enrollment keeps climbing and accreditation expectations keep tightening, the schools that treat placement visibility as infrastructure, on par with faculty hiring and curriculum design, will be the ones that scale without compromising the quality of the clinical education they provide.
To talk through what your program's placement data can and cannot currently show, and what dedicated recruiting infrastructure would change about both, get in touch with the NPHub university team.
Frequently asked questions
What is clinical placement data?
Clinical placement data is the structured record of every rotation a program runs, including the sourcing timeline, preceptor and clinical site credentials, compliance documentation, and the quality signals reported afterward. Strong placement data captures not only that a rotation happened, but how it was secured, whether the site and preceptor were verified, and how the clinical experience went. It splits into activity data (did it happen) and quality data (how well it happened).
What are the most important clinical placement metrics to track?
The most important metrics are time-to-placement and on-time start rate, preceptor retention across cohorts, site capacity utilization and specialty coverage, documentation completeness, student-reported placement quality, mid-rotation stability, and correlation with student outcomes such as completion and licensure pass rates. Together, they show whether a program's clinical placement process is fast, reliable, compliant, and producing genuine learning, rather than simply filling slots.
How do you measure clinical placement quality?
Placement quality is measured through feedback loops paired with outcome correlation: preceptor evaluations after each rotation, student surveys at mid-rotation and post-rotation, and site ratings that update over time. Those quality signals are then tested against student outcomes like completion, competency assessments, and licensure results, so a program can identify which clinical sites genuinely prepare students rather than merely hosting them.
What's a reasonable time-to-placement for an NP clinical rotation?
It varies widely by specialty, geography, and how sourcing is managed, ranging from a few weeks to several months. Programs that rely on faculty networks or student self-placement tend to see longer, less predictable timelines and more missed start dates. Tracking time-to-placement as a metric, and maintaining a continuous preceptor pipeline rather than starting outreach from scratch each term, is what shortens it.
Why are programs replacing spreadsheets with reporting systems for placement management?
Spreadsheets record placement data but do not reveal it. They are static, siloed, and cannot alert a coordinator to an expiring affiliation agreement, a lapsed credential, or a looming specialty shortage, and they break down as cohorts grow. Reporting systems give programs live status, automated alerts, and forecasting, turning clinical placement management from a filing task into strategic planning.
What placement data do CCNE and ACEN reviewers require?
Reviewers expect documented, repeatable, retrievable records: preceptor qualifications (licensure, board certification, clinical experience), current signed affiliation agreements, evidence that each clinical site was approved separately from the preceptor, and proof of ongoing oversight during the rotation. Expectations tightened after the Sawyer Initiative pushed CCNE to strengthen standards around site preparation and rotation quality. A good test is whether a program could produce full documentation on a random past rotation within an hour.
How does tracking preceptor retention help a program?
Preceptor retention, the share of preceptors who take a student again in the next cohort, is one of the clearest indicators of pipeline health. High retention means a program is building durable clinical partnerships and compounding its capacity; low retention means it is rebuilding its network every term, which is slower, more fragile, and more dependent on faculty effort. Tracking it early warns a program when relationships are eroding before a shortage appears.
Can a placement partner provide reporting that supports accreditation?
Yes, when the partner applies consistent vetting and documentation standards across every placement so that records are a byproduct of the work rather than a scramble before review. A partner that verifies licensure, approves clinical sites separately, and re-verifies over time can help a program produce audit-ready records on demand. Services built on open listings or basic credential checks generally cannot, so the vetting model is what determines whether the reporting is defensible.
Find a preceptor who cares with NPHub
Book a rotation