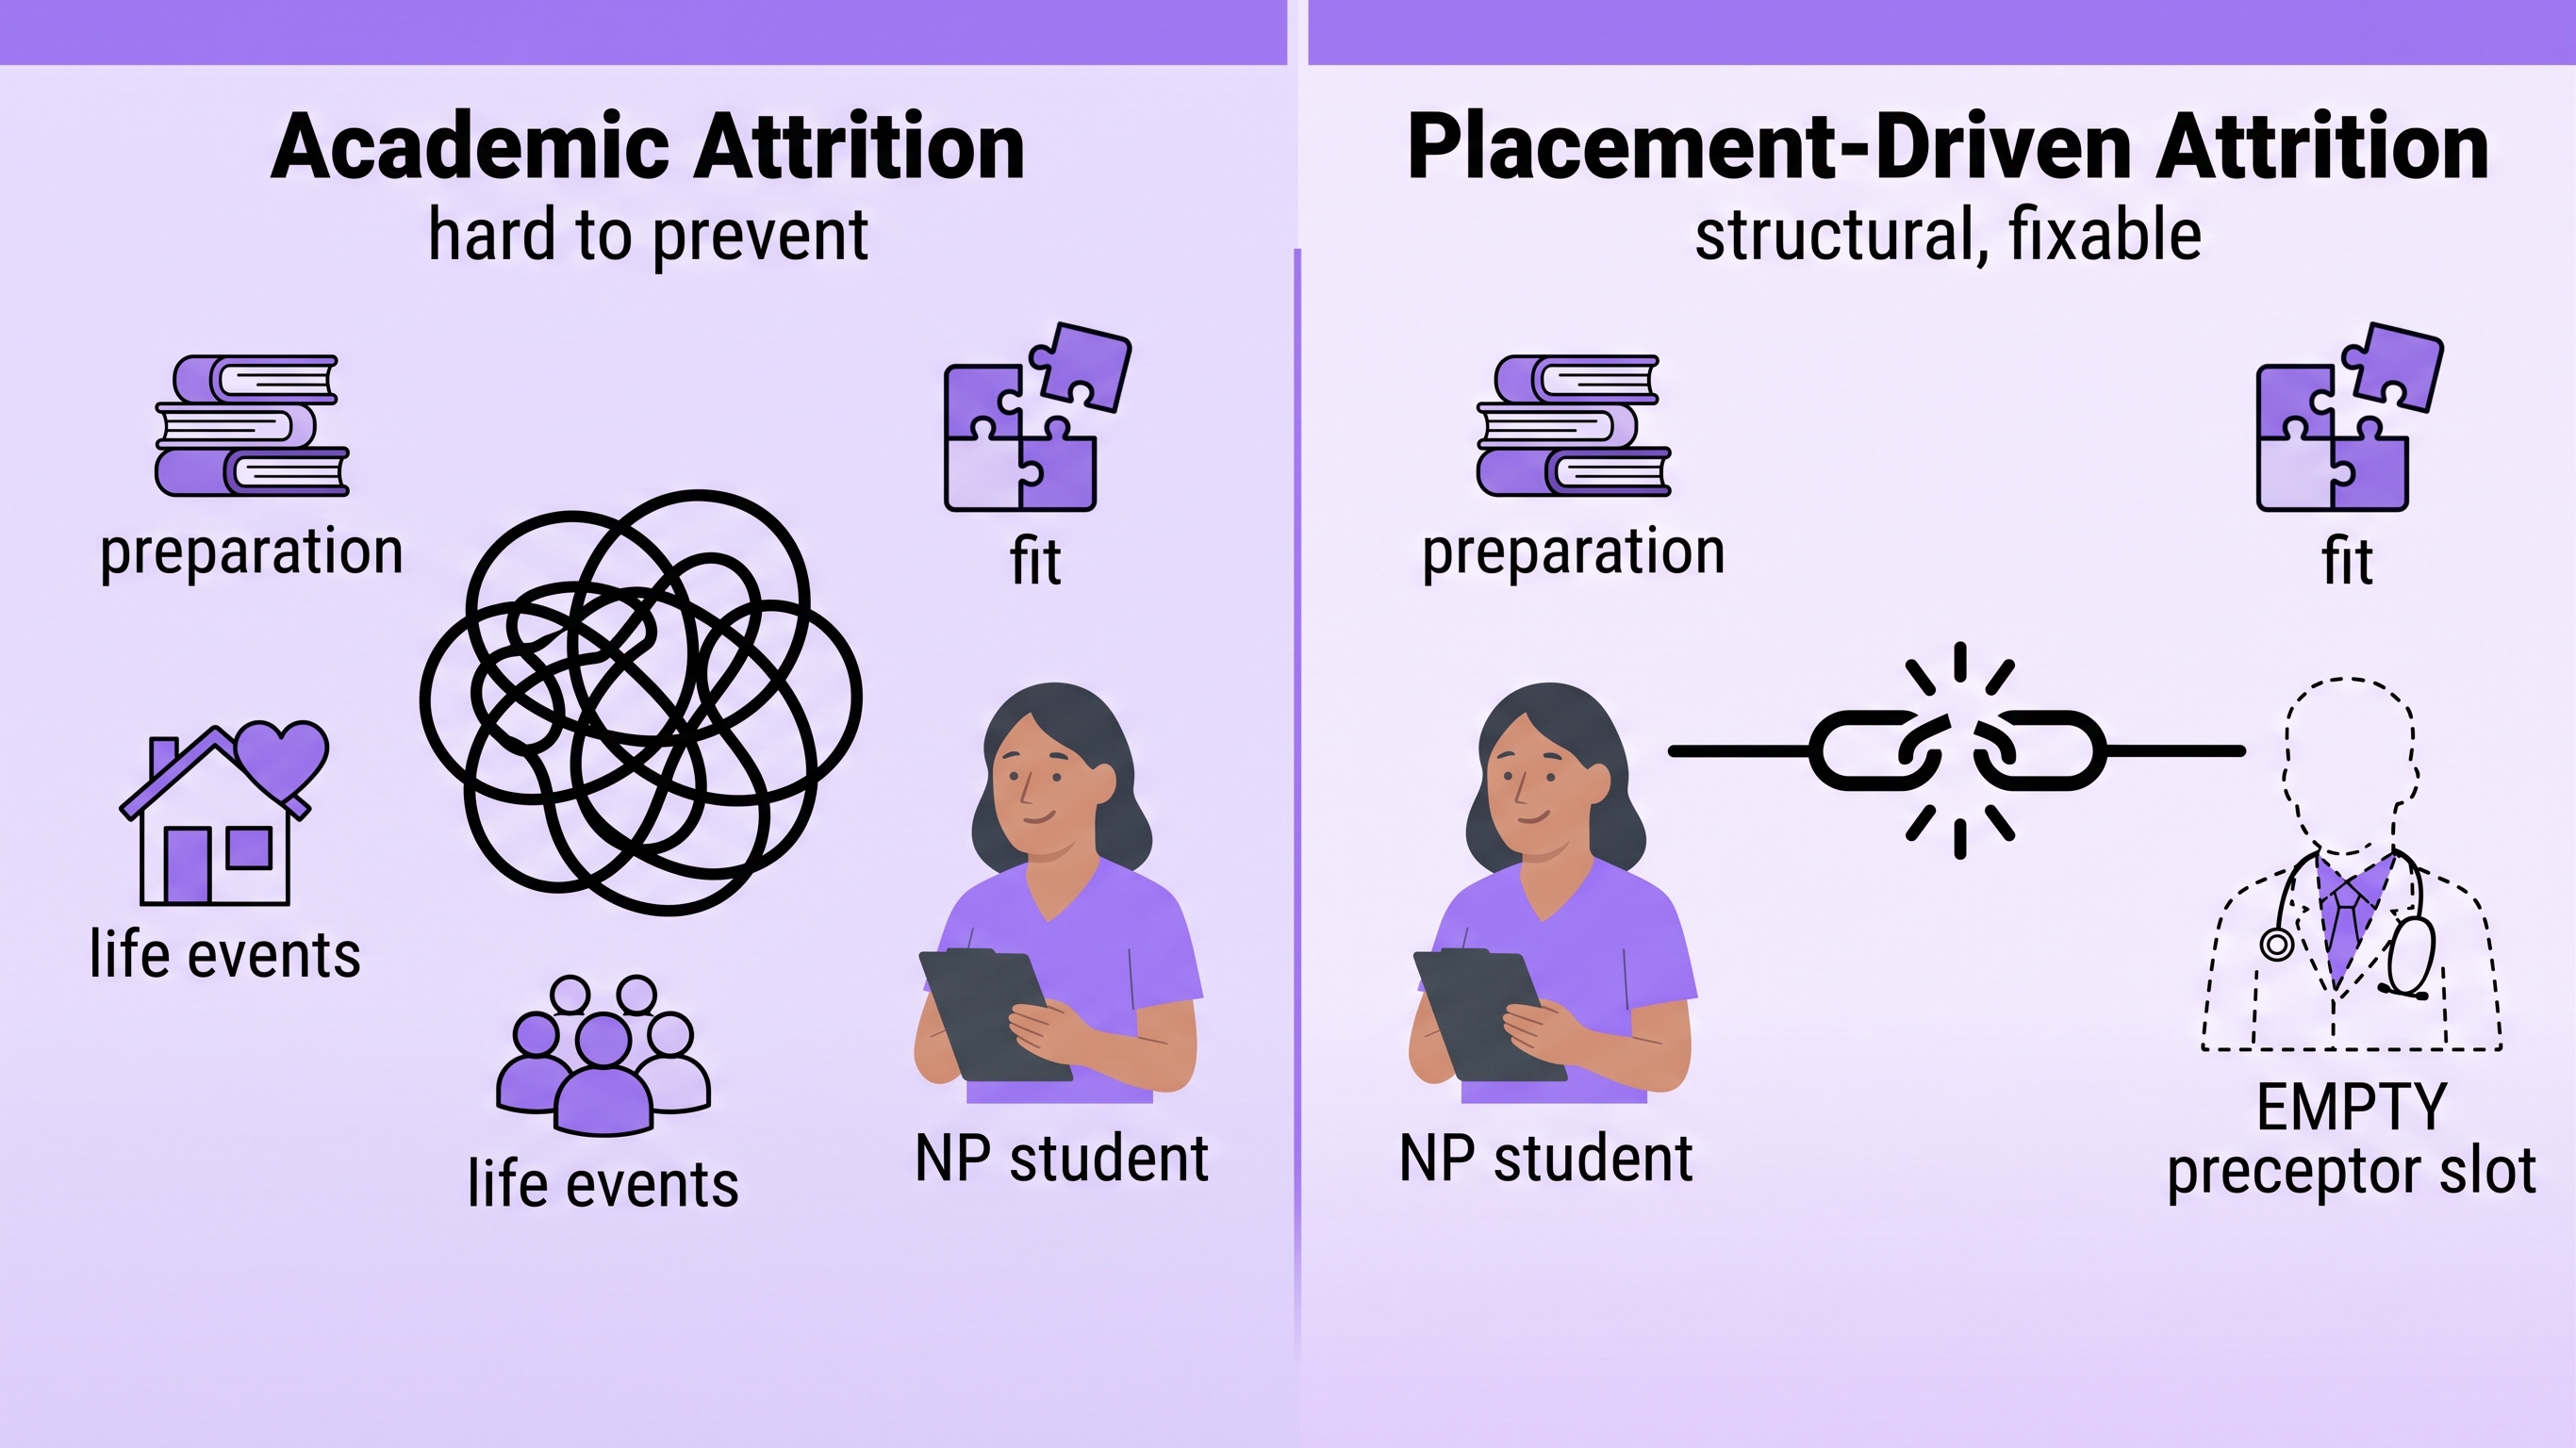



NP preceptors usually stop saying yes because precepting competes with productivity targets and patient load, and because too much surrounding work falls on them: unclear expectations, slow onboarding, paperwork, and underprepared students. Pay matters less than most programs assume. In recent preceptor surveys, clearly defined roles, supportive coworkers, and student EHR access outranked financial compensation. That makes NP preceptor retention a problem programs can actually influence. Programs that make precepting easy keep getting a yes.
TL;DR
- The NP preceptor shortage is as much a retention problem as a recruitment problem. Every experienced preceptor who quietly stops responding has to be replaced through new outreach, vetting, and relationship-building.
- Preceptors decline for predictable reasons. Time and productivity pressure, administrative burden, unclear expectations, underprepared students, and programs that go quiet after the placement is confirmed.
- Most retention levers sit inside the program's control. Student readiness, EHR access before day one, a single point of contact, formal preceptor training, and consistent check-ins.
- Incentives help, but they don't replace a good experience. Stipends, recertification credit, and state preceptor tax credits rank below role clarity and workplace support in what preceptors say keeps them precepting.
- What gets measured gets kept. Programs that track preceptor return rate alongside placement rate can see the pipeline leak before it becomes a placement crisis.
Most conversations about clinical placements start with the same question: how do we find more preceptors? It is a fair question. But for many NP programs, the more expensive problem is the preceptors they already had. The family nurse practitioner who took two students last year and doesn't answer this year's email. The pediatric site that hosted three rotations, then went silent after one difficult term.
Each of those exits resets the clock. Clinical faculty and coordinators go back to cold outreach, new credential checks, and new affiliation agreements for capacity the program already had.
This article is for program directors, clinical coordinators, and NP faculty who want to stop rebuilding the same pipeline every term. It covers why preceptors stop precepting, what the research says keeps them engaged, and how programs can build a preceptor experience worth repeating.
If keeping clinical placements steady from term to term is a challenge for your program, the NPHub university partnerships team can help you build a preceptor network that holds.
Is the NP preceptor shortage a recruitment problem or a retention problem?
It is both, but retention is the half most NP programs overlook. Recruiting new preceptors may get the attention, budget, and outreach. Keeping experienced preceptors engaged from one cohort to the next rarely gets its own plan.
The gap is not a lack of nurse practitioners. The American Association of Nurse Practitioners counted more than 461,000 licensed NPs in the U.S. as of November 2025. The gap is in how many of those practicing NPs precept, and for how long.
The NP preceptor landscape in numbers
- Demand keeps rising: AACN's 2025–2026 survey reports DNP program enrollment of 44,976 students, the 22nd consecutive year of growth.
- Capacity isn't keeping up: U.S. nursing schools turned away 93,176 qualified applications in 2025, including nearly 17,000 from graduate programs. AACN names insufficient clinical placement sites, faculty, and preceptors among the primary barriers.
- Most NPs aren't precepting: In a 2022 survey of 334 Texas NPs (Gigli & Gonzalez), 60% were not currently precepting, 37.6% said no one had ever asked them to precept, and 32.8% said their employer restricted precepting.
That last number matters for retention. Many practicing NPs are willing in principle but blocked by employer policy, productivity expectations, or a lack of contact from programs. The ones who do precept are a limited, valuable group, and losing them is costly.
NP programs aren't the only ones asking
NP programs compete for the same clinical sites and the same primary care providers as medical students, PA students, and other nursing programs. Published research on NP precepting describes this shortage as a direct driver of competition for clinical training sites. In that market, the program that is easiest to work with has a real advantage.
Why do NP preceptors stop saying yes to clinical rotations?
NP preceptors stop saying yes when precepting costs more than it gives back. The most common costs are lost clinical time, productivity pressure, administrative work, and the extra teaching load of an underprepared student. Most of these costs are shaped by how the program runs the rotation, not by the preceptor.
The clearest recent data comes from a 2025 survey of 73 FNP, PMHNP, and PNP preceptors at an Oregon DNP program. The researchers adapted an established preceptor incentive survey to rank what motivates and discourages clinicians who precept students. Their findings, and the studies they review, point to seven recurring reasons.
1. Precepting competes with productivity and direct patient care
Time is the barrier that shows up in nearly every preceptor study. A student slows clinic flow, and most practices don't adjust visit targets to account for teaching.
The pressure is sharpest in primary care, family practice, and urgent care settings, where schedules run tight and direct patient care is measured closely. In the Texas survey above, 12.4% of respondents said they weren’t precepting because it decreased their productivity, and nearly a third said their employer restricted precepting altogether. Preceptors in the Oregon survey rated protected teaching time as one of the most important factors in their decision.
2. It's usually unpaid, but pay isn't the whole story
Most preceptors are not paid for supervising students, and programs often assume that paying preceptors is the fix. The recent evidence says otherwise.
In the Oregon survey, personal financial compensation averaged 2.68 out of 5, and payment to the practice averaged 2.13. Both ranked well below role clarity and coworker support. Older studies found compensation mattered more, but post-pandemic research describes financial incentives as nice to have rather than decisive.
3. The paperwork lands on them
When onboarding is slow, the preceptor absorbs it. Delayed affiliation agreements, missing EHR access, and long student evaluation forms all turn into the preceptor's problem.
EHR access for students was the single highest-rated factor in the Oregon survey, at 4.53 out of 5. A student who can't log in on day one can't document, so the preceptor has to do the work twice.
4. Students arrive underprepared
Well-prepared, motivated students are one of the strongest reasons clinicians agree to precept again, according to post-pandemic research by DeClerk et al. (2024). The opposite is also true.
A student who isn't ready to work through a focused exam or an advanced pharmacology decision turns a teaching day into a remediation day. Preceptors are glad to support developing competency. They are less willing to fill gaps the program should have caught before the rotation started.
5. No formal preceptor training
Many experienced preceptors were never taught how to teach. They are expert clinicians who were handed a student and a syllabus.
Having the preceptor role clearly defined scored 4.00 out of 5 in the Oregon survey. Earlier studies found preceptors want formal preceptor training, clear guidance on student outcomes, and online resources. Research on NPs who haven't precepted yet shows many hesitate because they don't feel confident in the role.
6. Programs go quiet after the placement is confirmed
Clear expectations and ongoing communication from programs are consistent facilitators of precepting. When the only contact is a request in August and an evaluation form in December, preceptors feel used rather than partnered with.
The Oregon data adds a useful detail. Preceptors rated in-person faculty site visits low, at 2.74 out of 5. They don't need more visits. They need consistent, responsive contact by email or phone, and a person to call when something goes wrong mid-rotation.
7. Preceptor burnout, and one bad experience
Precepting is voluntary, so a single difficult rotation gives a tired clinician an easy reason to decline next time. Burnout makes that decision faster.
HRSA data cited in the Oregon study shows primary care physician burnout rose from 42% in 2020 to 49% in 2023. Supportive coworkers rated 4.07 out of 5 as a reason to keep precepting, which shows how much the clinical setting itself matters. A preceptor who feels unsupported at work and unsupported by the program is likely to stop saying yes.
Most of these reasons are fixable at the program level. The NPHub university team works with NP programs to take paperwork, mismatched placements, and follow-up off preceptors' plates, so the experience they have is one they'd repeat.
What happens to clinical placements when experienced preceptors walk away?
When an experienced preceptor stops precepting, the program loses more than one placement. It loses a vetted clinician, a known clinical setting, and a working relationship that took terms to build. Replacing that capacity means restarting the sourcing cycle.
Specialty gaps open first
The smallest preceptor pools feel the loss fastest. According to AANP’s NP fact sheet (based on its 2022 national NP database), only 2.4% of NPs held pediatric primary care certification and 2.2% held women’s health certification. Losing one experienced PNP preceptor or women's health site can leave a program with no local alternative.
Primary care is under pressure too. Research cited in the Oregon study reports that only 34% of NPs are choosing to practice in primary care following the pandemic, even though most NPs hold primary care certification. That narrows the pool of family nurse practitioner and primary care preceptors just as FNP enrollment keeps growing.
Student progress stalls
NP students can't progress without supervised direct patient care hours. The 2022 National Task Force Standards for Quality Nurse Practitioner Education require a minimum of 750 direct patient care clinical hours per NP track. When a returning preceptor drops out late, students wait for a replacement, and graduation timelines slip.
Site relationships weaken
Preceptors are often the program's main link to their healthcare facilities. When a preceptor leaves, the clinic manager, office staff, and affiliation agreement often go with them. A site that once hosted multiple rotations becomes a cold contact.
Losing a pediatric or women's health preceptor mid-cycle shouldn't put a cohort's clinical hours at risk. Talk with the NPHub university team about building specialty coverage that holds from term to term.
What makes a preceptor willing to precept again?
Preceptors come back when the rotation runs smoothly, and the role feels worth their time. Research consistently shows the deciding factors are operational, not financial. Programs that make precepting easy get asked back.
Across the Oregon survey and the post-pandemic studies it reviews, five factors stand out:
- A student who can work on day one: EHR access ready before the rotation starts was the highest-rated factor of all (4.53 out of 5).
- A clearly defined role: Preceptors want to know what the program expects of them and of the student (4.00).
- Support inside their own clinic: Supportive coworkers (4.07) and protected teaching time (3.81) ranked near the top.
- Prepared students and steady communication: Well-prepared students and clear, ongoing contact from the program are strong facilitators.
- Professional value: Preceptors rated learning from students who bring current clinical guidelines at 3.97, and credit toward certification or recertification at 3.62.
Underneath all five is something programs can't manufacture: most preceptors simply enjoy teaching. Enjoyment of precepting (4.32) and a sense of professional obligation to give back (4.15) were among the top motivators.
That is the real retention opportunity. The motivation is already there. Programs keep preceptors by removing the friction that wears it down.
The same data shows what doesn't move the needle. Acknowledgment at commencement (1.64), gifts of appreciation (1.66), and newsletter features (1.66) were the lowest-rated factors overall. Public thank-yous are kind gestures, but they are not a retention strategy.
How can NP programs improve NP preceptor retention?
NP programs improve preceptor retention by removing the friction that makes precepting costly: unready students, slow onboarding, unclear roles, and silence between placement requests. Each strategy below maps to one of the reasons preceptors stop saying yes.
Send students who are ready
A prepared student is the best thing a program can give a preceptor. Readiness is a program responsibility, not something to discover in week two.
- Confirm core clinical skills and advanced pharmacology readiness before the student is placed.
- Share the student's CV, prior clinical experience, and rotation objectives with the preceptor in advance.
- Set clear learning objectives for each rotation so the preceptor knows what "on track" looks like.
Take the paperwork off the preceptor
Every form a preceptor has to chase is a reason to decline next term. The goal is a rotation where the preceptor's only job is teaching.
- Assign a single point of contact for each preceptor and site.
- Execute affiliation agreements well before the start date.
- Complete EHR access and site onboarding before day one. It was the highest-rated factor in the Oregon survey.
- Keep student evaluations short, and tie each item to the rotation's objectives.
Offer formal preceptor training and CE credit
The National Task Force on Quality Nurse Practitioner Education's 2022 standards move NP education toward a competency-based model. That makes preceptor preparation more important, not less, because preceptors help evaluate clinical reasoning.
- Offer a short orientation or online module that explains the preceptor role, student expectations, and how to give feedback.
- Tailor it for first-time preceptors, who report the least confidence in the role.
- Help preceptors claim recertification credit. Under AANPCB's renewal rules, precepting can replace up to 25 non-pharmacology CE credits. Provide documentation of their hours without being asked.
Stay in contact before, during, and after the rotation
Preceptors don't need more site visits. They need predictable contact and a quick answer when something goes wrong.
- Before: an orientation email with dates, objectives, the student's background, and a named contact.
- Midpoint: a brief check-in by phone or email to catch issues early.
- After: a debrief, the student's evaluation results, and a direct question: would you precept next term again?
Recognize preceptors in ways that build their career
Oregon data clearly show that gifts and ceremonies don't retain preceptors. Recognition that adds professional value does better.
- Offer clinical or adjunct faculty titles that preceptors can list on their CV.
- Provide letters that document their teaching contribution for employers and credentialing.
- Encourage personal thank-you notes from students, which ranked second within the recognition category, behind enhancing credentials as a clinical teacher.
Rethink compensation, and talk to employers
Paying preceptors can help, especially in high-demand specialties. But stipends alone won't keep a preceptor whose rotations are hard to manage.
The bigger lever may be the employer. In the Texas survey, nearly a third of respondents said their employer restricted precepting. The researchers suggest programs educate employers on the preceptor role, the benefits of hosting students, and ways to balance productivity. Employers, not the program, provide protected teaching time.
Short-term vs. long-term retention tactics
Not every program has the staff to run all of these strategies in-house. The NPHub university team can show you which parts can be handled for you, from vetting and affiliation agreements to mid-rotation check-ins, so faculty can focus on teaching.
Do preceptor incentives and state tax credits actually work?
State preceptor tax credits help offset the cost of precepting, but there is little evidence they keep preceptors precepting on their own. In post-pandemic surveys, preceptors rate tax credits and financial incentives as welcome but not decisive. They work best as one part of a good precepting experience, not a substitute for it.
What state preceptor tax credits look like
Georgia became the first state to offer a preceptor tax incentive in 2014. Several states have followed, with very different designs:
Alabama and Maryland also run preceptor tax credit programs, and a federal bill, the PRECEPT Nurses Act, has been introduced but not enacted. Each program defines eligibility differently, so check the current rules before sharing them with preceptors.
Why credits alone don't solve retention
The preceptor data is consistent. McCann et al. (2024) found tax credits were among the lowest-rated motivators. DeClerk et al. (2024) found preceptors describe financial incentives as nice but not necessary.
There is also an operational catch. Most credits require that preceptors not be compensated for teaching. A program that pays a stipend may make its preceptors ineligible for their state's credit. Programs should know their state's rules before choosing a compensation model.
What professional organizations are pushing for
National organizations are working on the policy side. AACN supports the PRECEPT Nurses Act and other federal funding for nursing education, citing insufficient clinical sites and preceptors as primary barriers to admitting qualified applicants. HRSA's Advanced Nursing Education Workforce grants also fund preceptor recruitment and retention work, including the Oregon study cited throughout this article.
For programs, the practical takeaway is simple. Help preceptors claim the incentives they qualify for, and invest your own effort where the evidence points: role clarity, onboarding, and support.
How do regional preceptor partnerships keep clinical sites coming back?
Regional preceptor partnerships keep clinical sites engaged by making the relationship institutional rather than personal. When a program's connection to a site depends on one preceptor, it ends when that preceptor leaves. When it's built into an agreement between the program and the healthcare facility, it survives turnover.
Partner with the site, not only the preceptor
Supportive coworkers were one of the strongest reasons preceptors kept precepting in the Oregon survey. The study's authors recommend building relationships with clinic staff, administrators, and preceptors together, so the whole clinical setting supports hosting students. A formal site partnership makes that support easier to build than individual favors.
What durable academic-practice partnerships share
The nursing compendium Building Sustainable Academic-Practice Partnerships for Nursing Excellence reviews partnerships between schools of nursing and health systems. Its recommendations translate directly to sustaining regional preceptor partnerships:
- A formal memorandum of understanding with defined expectations and outcomes.
- A dedicated liaison who bridges the program and the clinical side.
- Regular, structured meetings between academic and practice leaders.
- Shared metrics, so both sides can see the partnership is working.
- Benefits for both partners, not only the school.
One example from the compendium is a long-standing partnership between a university school of nursing and its academic medical center in Alabama. In fiscal year 2023 alone, it supported 369 NP preceptor placements, and 140 hospital staff held academic appointments with the school.
Give the site something back
Partnerships last when the clinical site gains something too. In one documented partnership (Gustin et al.), a school of nursing and a children's health system built a COVID-19 call center staffed by 26 graduate nursing students, including pediatric nurse practitioner students. The school had used the hospital for undergraduate placements for years, but had no formal relationship for advanced practice students. After the call center launched, 71% of the system's primary care providers reported a drop in triage call volume at their practices.
The lesson is not the call center itself. It's that a site is more likely to keep hosting NP students when the program helps solve the site's own problems.
How should NP programs measure preceptor retention?
NP programs should measure preceptor retention the way they measure placement rate: every term, by specialty, with a named owner. The core metric is preceptor return rate, the share of last term's preceptors who agree to take a student again. Without it, a shrinking pipeline stays invisible until placements start failing.
Six metrics worth tracking
Ask preceptors why, not only whether. A short exit question ("What would make you precept again?") turns a lost preceptor into useful data.
Start with a one-term pilot
Retention work doesn't need a full program redesign to begin. A pilot with one cohort or specialty is enough to show what moves the numbers.
- Pick one cohort or specialty: Choose one where preceptor loss hurts most, such as FNP or PNP.
- Set a baseline: Record last term's return rate, time to placement, and on-schedule starts.
- Assign owners: A clinical coordinator owns the metrics. A faculty lead owns the preceptor relationships and check-ins.
- Apply two or three low-effort tactics: Start with EHR access before day one, a single point of contact, and midpoint check-ins.
- Compare at the end of the term: Ask every preceptor whether they'll return, and why.
Want a baseline before you pilot anything? The NPHub university team can help you benchmark preceptor return rates and time to placement against your cohort size and specialty mix.
How NPHub supports clinical preceptors so they keep saying yes
NPHub's preceptor recruiting function is built to remove the friction that drives preceptors away. Each part of the process maps to a reason preceptors stop precepting.
- Better matches from the start: Board-certified nurse practitioners vet every preceptor through a structured, 20-minute NP-to-NP interview covering scope, specialty, patient population, and teaching readiness. Fewer mismatched rotations mean fewer bad experiences.
- Preceptors choose how they precept: Preceptors set their preferences, choose the students they take, and set their schedules, so precepting fits around their patient care rather than competing with it.
- Paperwork handled: Affiliation agreements are secured, and clinical sites are approved separately from individual preceptors, so the administrative work doesn't land on the clinician.
- Contact throughout the rotation: Check-ins at the start, midpoint, and end of each rotation surface issues early, before they turn into a reason not to return.
- Problems resolved fast: Active preceptors and sites are re-verified every 45 days. Through the Perfect Preceptor Promise, we provide a replacement at no additional cost if a placement doesn't work.
For programs, the result is a preceptor network maintained across cohorts rather than rebuilt each term, with documentation built in along the way.
To see how this process would fit your program's rotations and accreditation documentation, connect with NPHub's university team, led by Director of Business Development Nicholas Carrizales.
Conclusion: Retention is the most affordable capacity a program can build
The NP preceptor shortage won't be solved by recruitment alone. Programs can keep adding new names to the list, but if experienced preceptors quietly leave at the same rate, capacity never grows.
The evidence points somewhere useful. Preceptors mostly want to teach. What pushes them out is friction programs can control: students who aren't ready, onboarding that drags, roles nobody defined, and silence between requests. Pay and public recognition matter less than most programs assume.
Fix those, and precepting becomes something clinicians want to repeat. That protects student progress, clinical faculty time, and quality nurse practitioner education. It also protects the future healthcare workforce that depends on today's preceptors.
Every preceptor who comes back is a placement you don't have to rebuild. If you're ready to make precepting easier for your clinical partners, the NPHub University team is a good place to start that conversation.
Frequently asked questions
Why do NP preceptors stop precepting?
NP preceptors most often stop because precepting competes with productivity targets and patient load. Other common reasons include administrative burden, unclear expectations, underprepared students, and limited support from their employer or the program. A single difficult rotation can be enough for a busy clinician to decline the next request.
Should NP programs pay preceptors?
Paying preceptors can help, but recent research suggests pay is not the main reason preceptors stay. In a 2025 survey, preceptors rated financial compensation well below role clarity, coworker support, and student EHR access. Programs should also check state rules, because many preceptor tax credits apply only to preceptors who are not compensated.
Which states offer tax credits for NP preceptors?
Georgia, Colorado, Alabama, and Maryland have offered preceptor tax credit programs, and other states have proposed them. Georgia currently offers APRN preceptors $750 per 160-hour rotation, up to 10 rotations per year. Amounts and eligibility vary widely, so confirm current rules with each state's program office.
Do NPs get CE credit for precepting?
Yes, in many cases. Under AANPCB renewal rules, precepting can replace up to 25 non-pharmacology CE credits toward recertification. Other certifying bodies have their own rules, so preceptors should check with their certifying organization.
What training do NP preceptors need?
Requirements vary by program and state, and many practicing NPs who precept have never had formal preceptor training. Research shows preceptors want a clearly defined role, guidance on student expectations, and practical resources on giving feedback. A short orientation module, tailored for first-time preceptors, covers most of that.
Can physicians in family medicine or internal medicine precept NP students?
Many NP programs accept physician preceptors, depending on program and state requirements. In the 2025 Oregon survey of NP preceptors, about 15% held an MD, with specialties including family medicine and internal medicine. Programs should confirm who qualifies as a preceptor under their own policies and their state board's rules.
How can programs reduce preceptor burnout?
Programs reduce preceptor burnout by lowering the workload that precepting adds. That means sending prepared students, completing EHR access and paperwork before day one, defining the preceptor role clearly, and checking in regularly. Working with employers on protected teaching time addresses the biggest barrier: lack of time.
What do preceptors want from an NP student?
Preceptors want students who arrive prepared, with core clinical skills, a working knowledge of pharmacology, and clear goals for the rotation. Well-prepared, motivated students are one of the strongest reasons clinicians agree to precept students again. Preceptors also value students who bring current clinical guidelines into the practice.
How do programs keep preceptors across multiple cohorts?
Programs keep preceptors by making each rotation easier than the last. Track preceptor return rate every term, ask preceptors directly whether they'll return and why, and fix what they report. Formal site partnerships help too, because they keep the relationship going even when an individual preceptor changes roles.
Find a preceptor who cares with NPHub
Book a rotation